Activities
Training workshops
Trauma care in the context of limited resources needs skills in diagnostics and context-adapted treatment plans. A special focus should be on conservative treatment, cast immobilization, skeletal traction and the use of external fixator. Reduction of fractures without c-arm is another aspect to be considered. In a workshop for basic trauma care, lessons adapted to the rural trauma surgeons need are accompanied by skills stations for the use of external fixator, tendon reconstruction and auto-production of atraumatic sutures with fishing line and needles. Visiting other institutions (Prosthetics Workshop of the Government Hospital, NGO that manufactures fuel-efficient cook stoves) is part of the networking, to widen the view to postoperative care and burns prophylaxis.
Assisting in orthopedic surgery
Teaching in the local environment with locally available equipment to care for local conditions is one key principle. In Madagascar a friendship of more than 20 years exists with the PAACS-trained experienced surgeon at Antsirabe (PAACS stands for Pan African Academy of Christian Surgeons). He is the cornerstone of teaching the next generation of surgeons. Teaching by example, practicing sound communication along with a thorough knowledge of the problem and the various solutions are essential components. To be complete, every surgical case should follow a preoperative plan and a postoperative follow-up. The use of the WHO Checklist for Safe Surgery, writing a postoperative documentation and instructions for postoperative treatment are important steps as well.
Instruments, equipment for basic trauma care
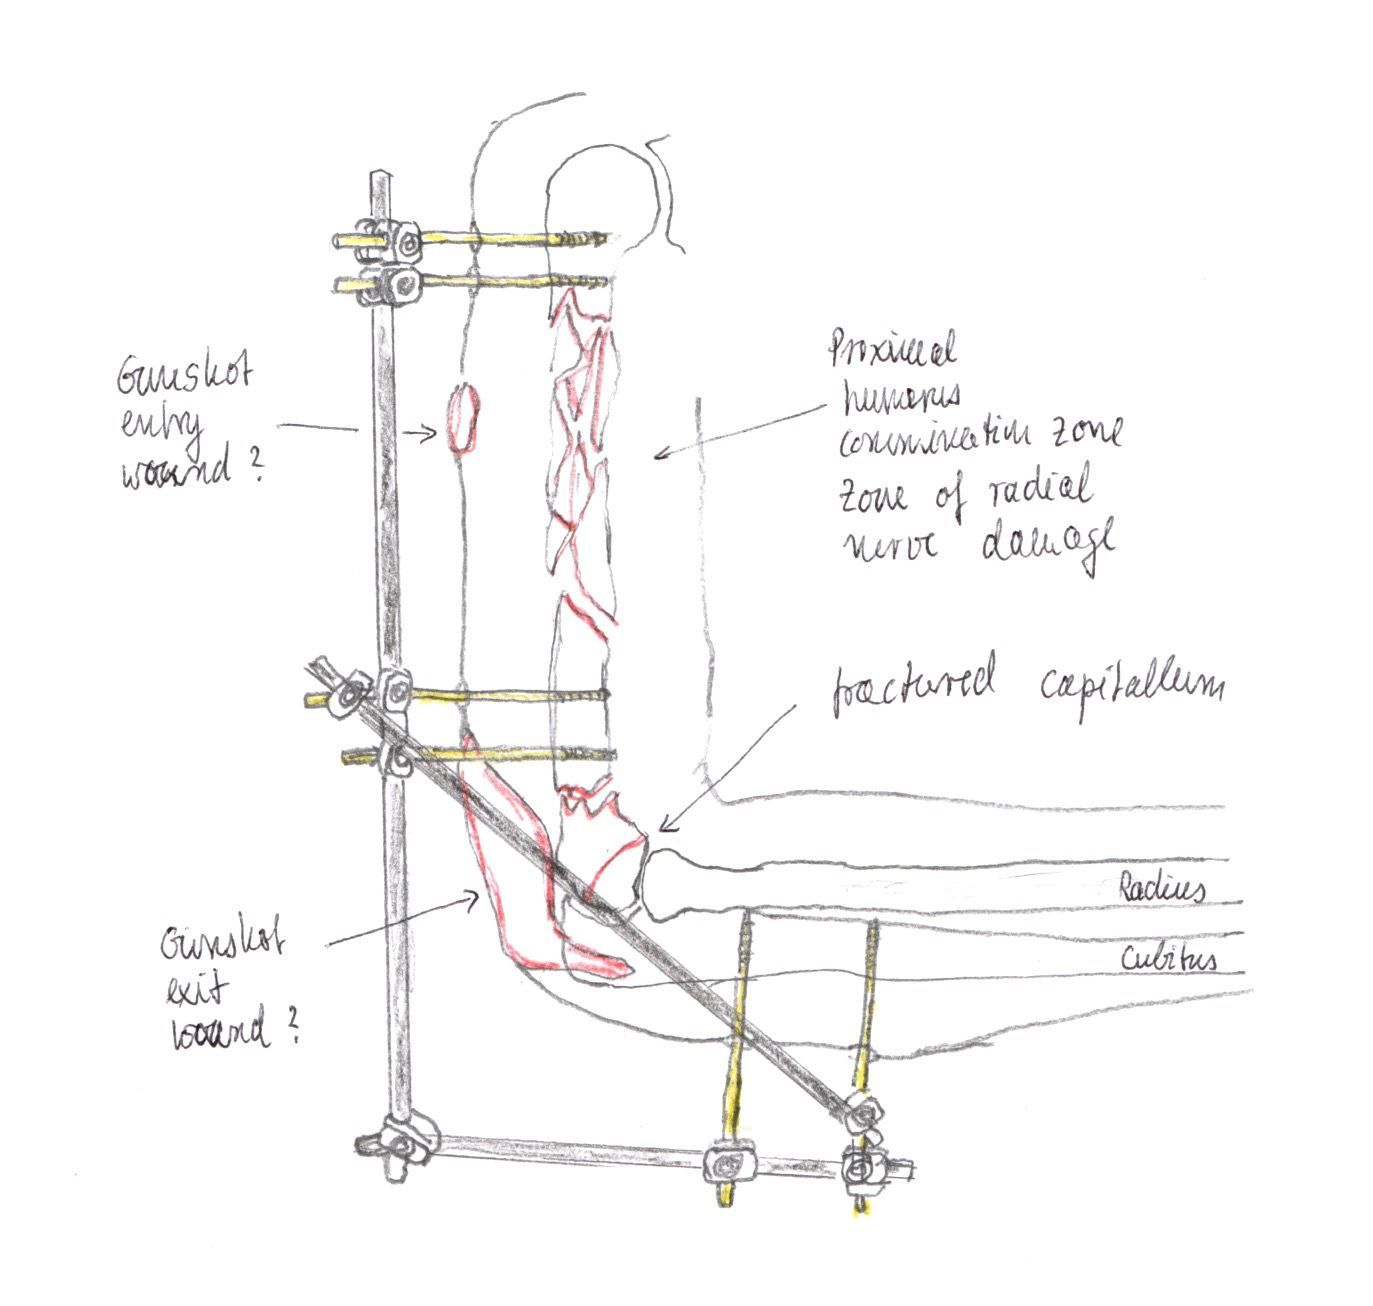
When talking about orthopedic trauma surgery, we have to keep in mind that sterility is crucial in the operation room. When intramedullary nailing and bone plating are done, the sterility has to be on an excellent level. For many hospitals basic equipment like external fixator and K-wires are an alternative to be considered. This allows for stabilization of open or comminuted fractures with limited risk of infection. To apply an external fixator, a power drill is necessary. The simplest solutions are context appropriate battery-operated power drills. When we talk about open fractures and their often-late presentation serial debridement might be necessary. A debridement set with chisels and bone curettes must be part of the basic equipment set, as well as instruments for skeletal traction, skin graft and amputation.
Advocating the SIGN nailing system
As an answer to the rising numbers of trauma victims in the Global South the American orthopedic surgeon Lewis Zirkle developed the SIGN nail and created SIGN Fracture Care International. This organization builds sustainable orthopedic capacity in the Global South by providing relevant education to surgeons, then manufacturing and donating the instruments and implants needed to treat fractures. The SIGN surgeons report the injury, the surgery performed including x-rays and the controls at 6 weeks and 6 months. This runs into the huge SIGN database.
The SIGN nail system can treat fractures of humerus femur and tibia. A fin nail and a SIGN pediatric nail are also available.
I learned the SIGN nailing technique at the Muhimbili Orthopedic Institute in Dar es Salaam, Tanzania ant at St. Orsola Hospital, Matiri, Kenya. In Cameroon I supported the implementation of the SIGN technique at the Lutheran Hospital of Ngaoundéré.
When introducing intramedullary nailing, be aware of the sterility requirements in the OR.
Context-adapted equipment
To avoid broken medical equipment piling up in a remote storeroom, the donation as well as the purchase should be done with care. Those are steps to follow, making equipment work for its lifetime:
- Planning and procurement: New equipment meets clinical needs, that are identified by the medical team of the hospital and are in line with a standardization effort of the health department
- Installation in reliable infrastructure to operate the equipment: stable power and water supply
- Practical training: for clinical staff (user training) and for the technical staff who maintain it
- Maintenance systems: team of trained hospital technicians with a workshop, tools, information resources and spare parts
Image: Diamedica Glostavent® Helix at the SICA-Hospital of Doctors without Borders, Bangui, RCA. The MSF standard anesthesia machine is equipped with a built-in ventilator and an oxygen concentrator (no external gas needed). It can operate without power supply for a limited period of time. Available from Medical Aid International.
Tools for patient security, organization and quality of care
- The WHO Checklist for safe surgery is a barrier to prevent perioperative adverse events. It has shown its efficacy over decades in various surgical environments. In those with limited resources a poster-like laminated version, fixed to the OR-wall, allows for visually going through the checklist and documenting it in the patient's file.
- Standard Operating Procedures have gained wide acceptance in medical care. 5 reasons to develop SOPs: transfer of knowledge - quality control - performance - patient security - standardization. Teaching for example skeletal traction is more sustainable if, the team can rely on an SOP in the daily work.
- Standard treatment protocols help in the correct use of antibiotics for perioperative prophylaxis and treatment of surgical infections. The MSF Clinical Guidelines are an excellent resource for a variety of conditions. The financial accessibility of the treatment for patients often limits the adherence to a protocol and needs sound judgment for an adapted approach.
Telemedicine
The worldwide web allows for remote tutoring, using WhatsApp together with the surgical teams of SALFA hospitals and the tele-medicine platform of ‚Doctors without borders‘ (MSF) fir MSF teams worldwide.
In the
WhatsApp group ‚Traumatologie Hôpitaux SALFA‘ anonymised patient cases can be presented, x-rays and clinical images uploaded and treatment strategies discussed. For doctors of SALFA hospitals, this allows a team approach to orthopaedic trauma. The propositions made in this WhatsApp group often lead to additional imaging, a better diagnostic insight and sound treatment strategy. The photo shows a 1-year-old child with femur fracture, treated with overhead traction. The wooden traction device was made by the hospital’s carpenter following the shared documents.
The interconnected
MSF telemedicine platform
allows data to be exchanged in order to provide medical care for patients in remote areas. Any MSF medical team can upload data such as clinical data and images to the platform, where participating specialists are able to access the data and help make a diagnosis. As specialist of orthopaedic trauma, I participate with paediatricians, infectiologists, radiologists and others in the discussion. The team that presented the case hopefully gives updates and informs on the patient’s evolution. Having worked in hospitals with limited resources helps me to tailor a context-adapted advice.
Biomedical Service support for SALFA
The founder of the Health Department of the Lutheran Church (SALFA), Dr. Stanley Quanbeck had not only built the SALFA headquarter at Antananarivo, but also integrated a Maintenance Service with two maintenance technicians. Due to retirement these technicians are no longer available. In order to rehabilitate this service, two SALFA employees have received the biomedical training offered by the MedAid Academy of MedAid International. They are both working at the SALFA Headquarter. Two biomedical technicians cannot cover the needs of 10 hospitals, dispersed all over the island. Another approach might be necessary: the establishment of a Biomedical Service for SALFA.
Effective and appropriate management of healthcare technology will contribute to improved efficiency within the SALFA health service. This will result in improved and increased health outcomes, and a more sustainable health service. This is the goal of rethinking SALFA’s Biomedical Service. Each hospital needs maintenance teams and trained maintenance technicians to do the routine works of preventive maintenance, user training and corrective maintenance as needed. The vital infrastructures of the hospitals as water supply, electricity also fall in their reasonability. My participation is to open corridors to biomedical knowledge and training for the SALFA Management Team:
- HUMATEM in France offers consultancy for biomedical service building
- MedAid Academy offers biomedical Training
From random donations to procurement per order
Orthopaedic trauma surgery is relies on access to implants and consumables as plates, screws, elastic nails, K-wires, drill bits, external fixator components and other consumables. The SALFA surgeons rely on donations from the partner oranizations and from visiting surgeons. This method of procurement often leeds to situation where the correct length for scews or plates are not available. The surgeon has to shift to another way of treatment, to transfer the patient or to cut the available implants to the needed lenth. The photo above shows the cutting of a plate on the room next to the operating room.
The donation-based procurement should
shift to an order-based procurement to reduce out-of-stock situations and constraint of sub-standard management of cases.
To allow for the placement of orders I have provided PDF forms to the SALFA surgeons, that list the relevant consumables for orthopedic trauma surgery with their name ,size, and order number of the supplier, which is a relieable supplier in India.
THe NGO 'Doctors for Madagascar' has set up a Fund for Safe access to surgery and anesthesia to pay for these orders, as long as the fund is sufficiently filled.
The price of surgical consumables is much lower in India than in contries of the Global North.
This initiative is a step towards more equitable access to surgical care.
If you want to support this initiative add 'Access to safe surgery and anesthesia ' to your donation.
